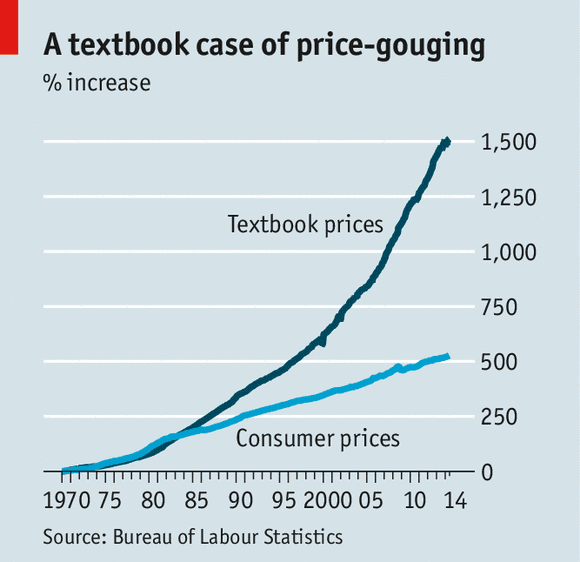
From an article in the Economist.

19/08/2014
Post Link
(credit: http://en.wikipedia.org/wiki/Dynabook)
I came across this picture of Alan Kay via the Monday Note. Kay is a Turing award winner, and somebody who has thought more deeply than anybody else I know about learning, and the use of computers in learning. The picture was taken in 2008 but his Dynabook was developed in 1972. It does not take much imagination to realise the relation between the physical Dynabook and the iPad. In academia ideas are almost everything — we prize them above all else for most types of work. But execution and product delivery matter as much is many domains. Ideas are cheap in education, but delivery is our main bottleneck. As Jean-Louis Gassee comments in a slightly different context: ‘We both understand that ideas are just ideas, they’re not actual products. As Apple has shown time and again — and most vividly with the 30-year old tablet idea vs. the actual iPad it’s the product that counts’. I think most sensible ideas about learning will come from building the artefacts.
19/08/2014
Post LinkPerhaps unsurprisingly, researchers working in fields where the accumulation of relatively small bits of new knowledge is valued, such as medical science, accounted for the majority of those in the influential core in a random sample of the data.
An article in the Times Higher, reporting some research by the ever productive John Ioannidis. Another ‘brick in the wall’, as Pink Floyd sang.
14/08/2014
Post LinkWell, no longer are students just consumers or clients, so I shouldn’t be surprised. The Time Higher (24/7/2014) reports that firms are offering graduating students digitally enhanced photographs at graduation. Body sculpting, complexion enhancement and smile enhancement, all available at low cost. Less is hidden than with many an honorary degree, perhaps…
13/08/2014
Post Link
Derek Bok, Universities in the Marketplace, Princeton University Press, 2003]
13/08/2014
Post LinkI seem to remember it was a junior doctors’ mess room game to express amusement at some doctor’s surnames (Mr Butcher, the surgeon; Lord Brain the neurologist; Dr Child, the paediatrician etc). The other thought experiment related to collective nouns for groups of staff. A ‘scab’ of dermatologists; a ‘clot’ of haematologists; a callus of orthopaedic surgeons, and so on. For professors, it was simply ‘absence’— an ‘absence of professors’. The THE has wondered what the term might be for university Principals (Vice-Chancellor or Presidents). The noun is ‘lack’, as in a lack of Principals.
12/08/2014
Post Link11/08/2014
Post LinkThe Economist (Tescopoly no more) tells me that Aldi stock around 1,500 products and Tesco supermarkets 40,000. The article implies this is one of the reasons Tesco is ‘in trouble’. What about your hospital or medical school: which one are you?
07/08/2014
Post LinkCouple of papers on generalist versus specialism crossed my desk. One in the BMJ (Munro et al, page 3 in the Careers section; and a debate pair of articles in Clinical medicine, by Firth and Fuller, Clin Medicine,(2014) 14;(4) p354 and 357. The articles in clinical medicine are well worth reading, although very focussed on the nightmare that is general medicine / acute takes (sadly, the online version of the RCP journal lags behind the paper version: a bit like the RCP). From a narrow dermatological perspective, much of what has been suggested in the Shape of Training review is flimsy, and parochial, and dominated by what I think is an out of date UK perspective on medical practice. The UK model is no longer an example for much of the world. There are however some general points worth thinking about whenever people trying and fit medics into a binary divide of ‘specialist or generalist’.
Medicine is fractal, we can move from being a primary care doctor who sees all age groups, through to primary care doctors who see (say) just children. Once you think about specialists, there are degrees of generalism. A dermatologist may see rashes and tumours, or be a surgical dermatologist and just see tumours. You may be a paediatric dermatologist, and not see adults, and a general paediatric dermatologist will refer patients with rare disorders such as xeroderma pigmenta to other sub-specialists, or to those with expertise in genodermatoses. If there is room for only one doctor to look after a bunch of scientists ion the Antarctic, we can think hard about what skills are needed, but they are not the same skills as a generalist primary care doctor in Morningside. When you have a lens, you see more detail; when you have a light microscopy you see yet more; when you have a scanning electron microscope, you see even more. The richness and knowledge needed of natural history, and therapy, is fractal.
The second point is that continued expertise is not just a feature of certification or historical accreditation, but of continued exposure. You can educate GPs all you like about melanoma (if I were a GP, I would find the terminology patronising, but I am repeating what others say), but if your exposure to true cases is ~ 1 every 10 years (such as for melanoma), there are experiential limits on competence. I do not know the shape of the function of competence against exposure, but I do not believe it to be linear. Part-time working also has to be considered.
Specialism comes with transaction costs if mis-referral happens, and those with blinkers do not see the error of their ways; or fails when the signal to noise ratio is too low to allow segmentation of the target group. Conversely, in anything but a small population, it would be bizarre to think that medicine would be immune to the advantages of specialism that, as much as anything else, have led to the scientific revolution and the modern industrial state.